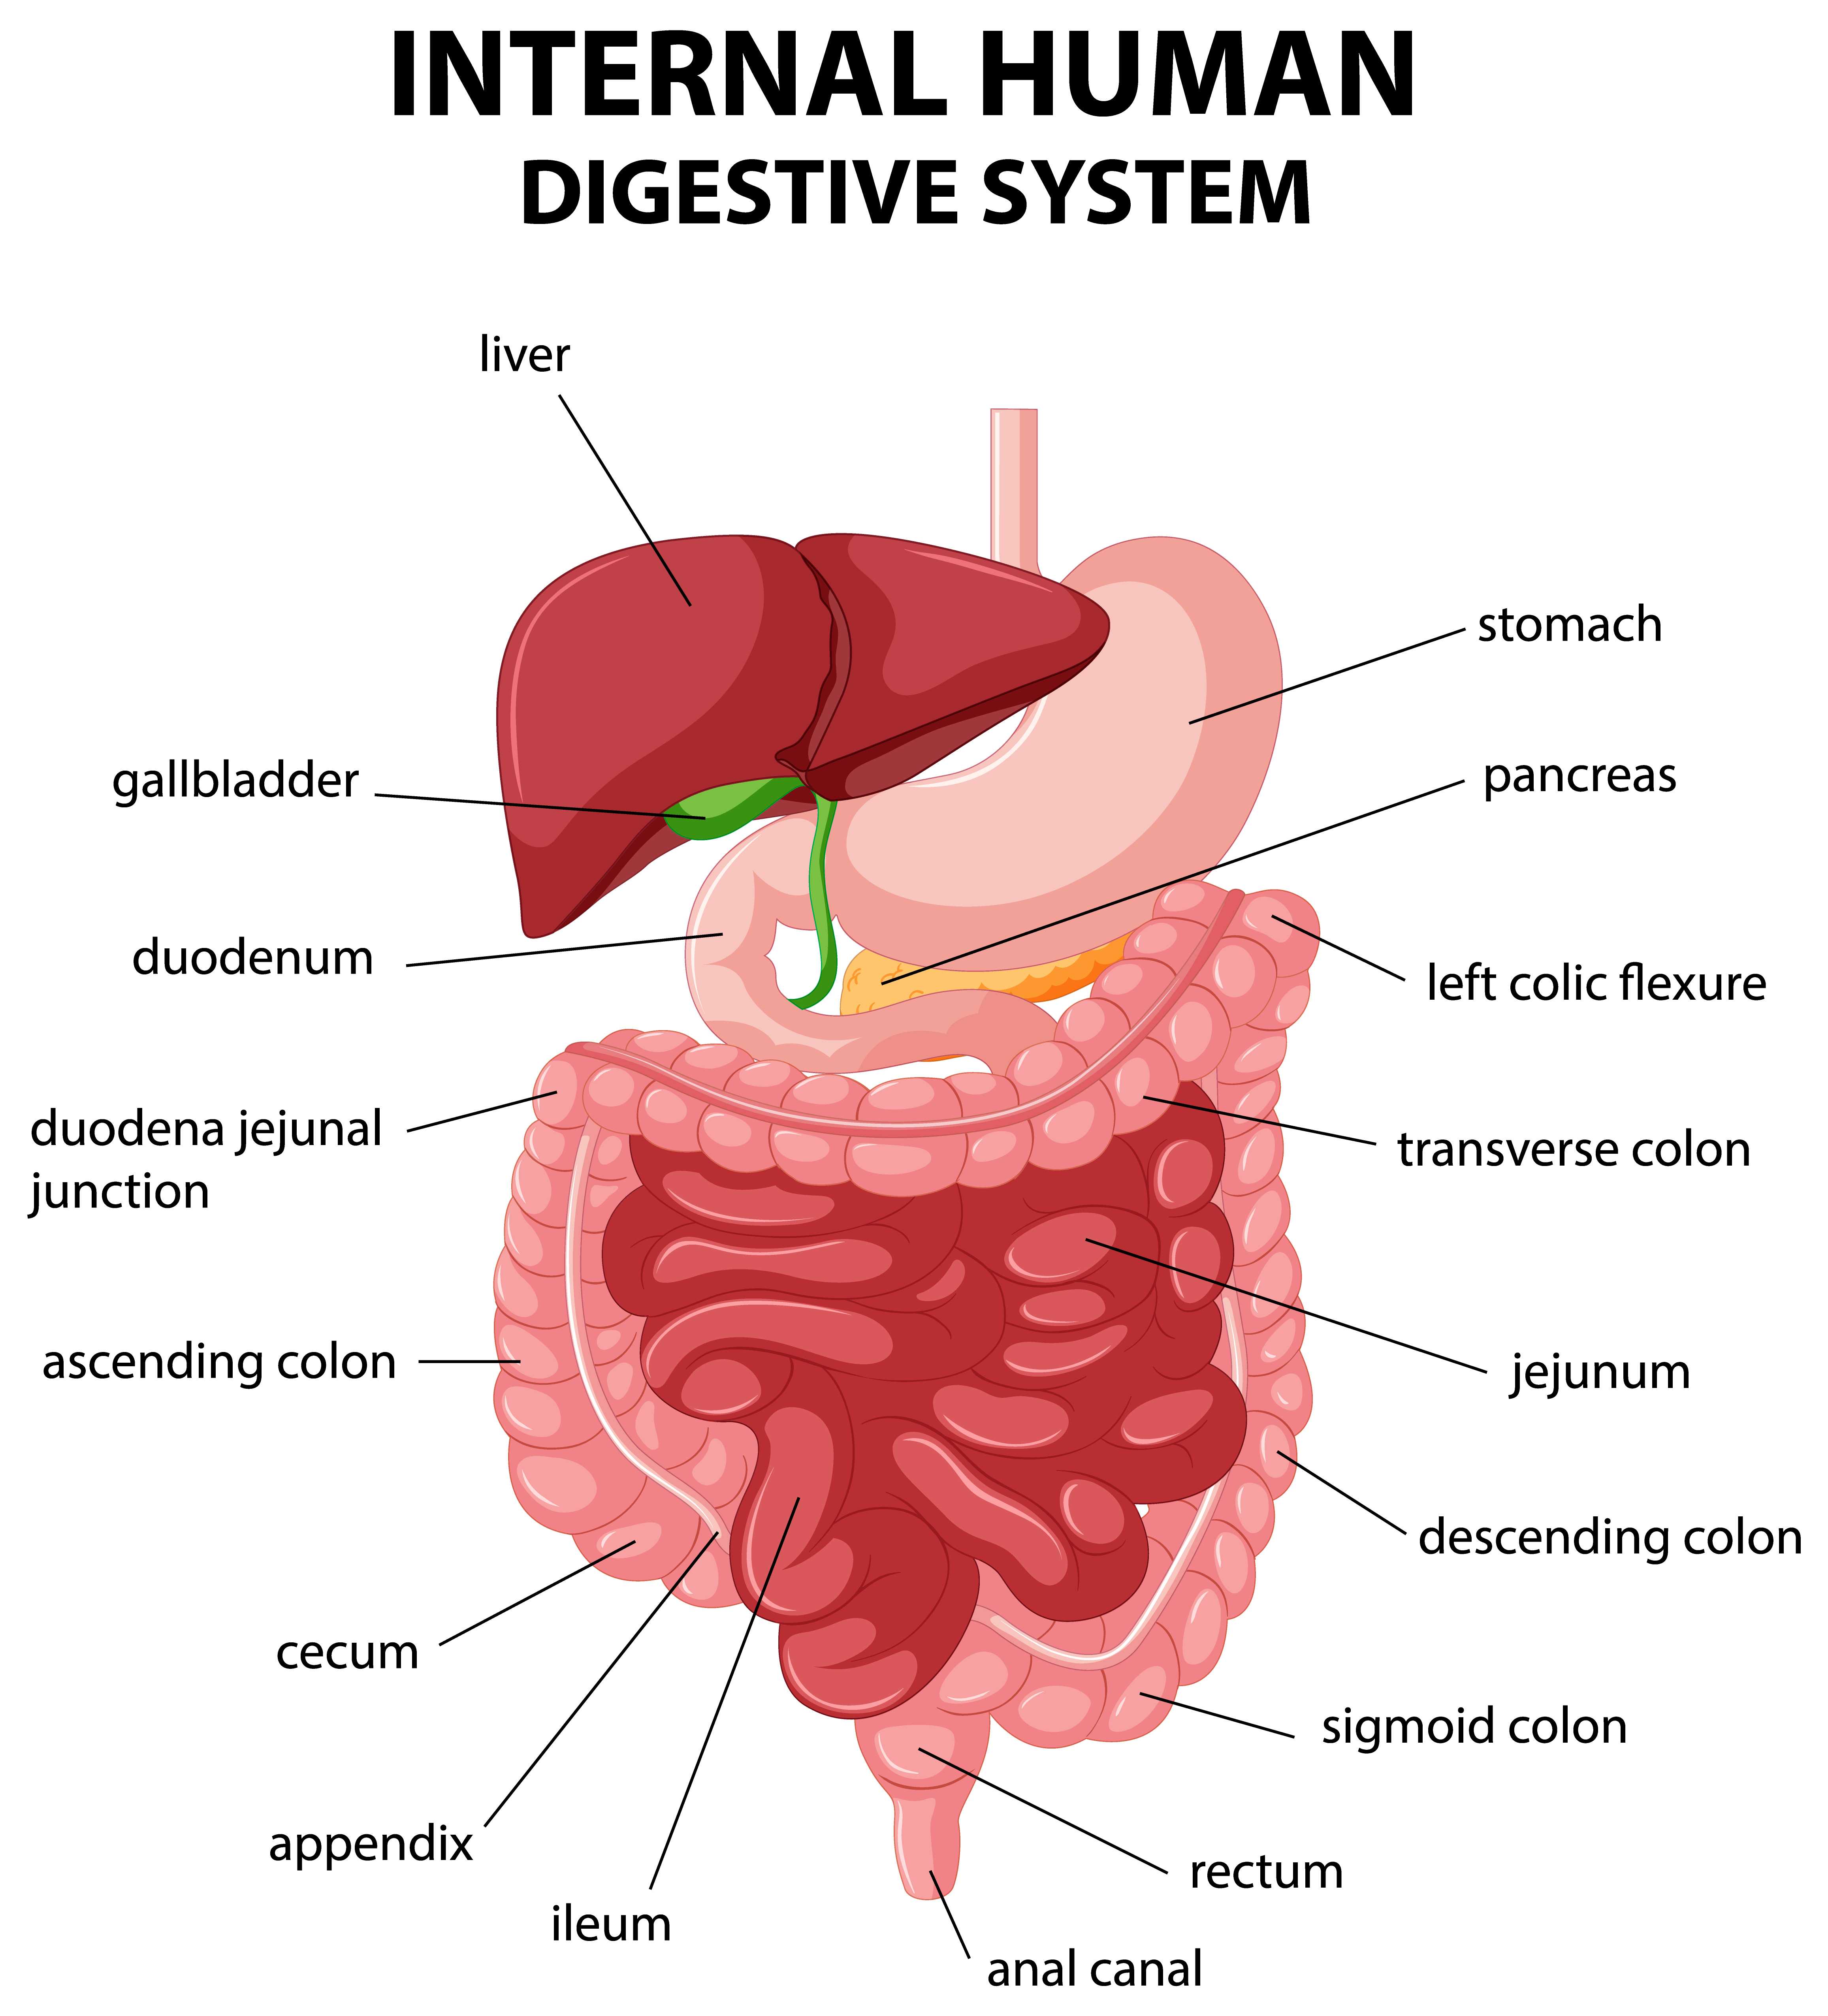
Medical infographic explaining irritable bowel syndrome (IBS), including symptoms, triggers, and management tips.
Irritable Bowel Syndrome (IBS) is one of the most common and most frustrating gastrointestinal conditions. It affects an estimated 10–15% of the Indian population — hundreds of millions of people — yet remains underdiagnosed because its symptoms mimic other conditions, vary widely between individuals, and are often dismissed as "just stress" or "sensitive stomach."
IBS is a real, recognised medical condition. It causes genuine physical discomfort and can significantly impact work, social life, and quality of life. And while it has no cure, it is very manageable with the right approach.
What Is IBS?
IBS is a functional gastrointestinal disorder — meaning the bowel's structure is normal on investigation (no visible inflammation, infection, or structural abnormality), but its function is abnormal. The gut-brain axis is dysregulated: signals between the digestive system and the brain are altered, producing abnormal bowel motility, heightened visceral sensitivity (the gut is more sensitive to pain and discomfort than normal), and disturbed gut-brain communication.
IBS is not:
Inflammatory bowel disease (Crohn's disease or ulcerative colitis — which cause actual inflammation visible on colonoscopy)
Coeliac disease (gluten intolerance — a structural gut reaction to gluten)
A psychological disorder (though psychological factors influence it)
IBS Symptoms
IBS is characterised by recurring abdominal pain associated with changes in bowel habits — this combination is the diagnostic core.
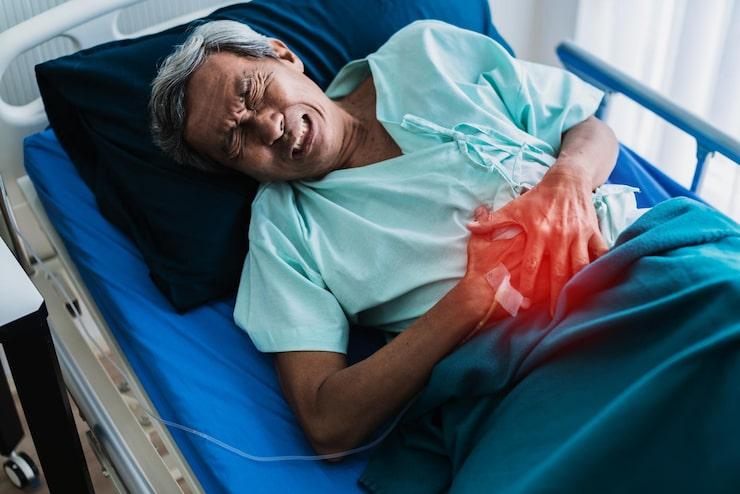
Abdominal pain or discomfort
Cramping, aching, or sharp pain — typically in the lower abdomen, though it can be anywhere
Often comes in waves or cramps
Characteristically relieved by passing stool or gas — this association with defecation is a key IBS feature
Related to changes in stool frequency or form
Present for at least 1 day per week on average over the last 3 months (Rome IV diagnostic criteria)
Changes in bowel habit
IBS is classified by the predominant bowel pattern:
IBS-D (diarrhoea-predominant): frequent, loose or watery stools; urgency; fear of not making it to the toilet in time
IBS-M (mixed): alternating between constipation and diarrhoea — very common, and very disorienting
IBS-U (unclassified): doesn't fit neatly into the above patterns
Bloating and gas
Abdominal bloating — a sensation of fullness or distension — is present in the vast majority of IBS patients, often as one of the most distressing symptoms. Visible abdominal distension (the abdomen actually gets larger through the day) is common. Excessive flatulence is common. The bloating in IBS often worsens through the day, is worse after eating, and improves after sleeping.
Mucus in stool
Clear or white mucus in or on the stool is common in IBS. It's the mucous membrane lining producing excess mucus — not a sign of blood or infection.
Urgency
Particularly in IBS-D: sudden, urgent need to defecate that may be difficult to defer. This creates anxiety around being away from a toilet — restaurants, commuting, meetings, social events all become sources of stress.
Fatigue
Often underappreciated. IBS is associated with persistent fatigue that may relate to poor sleep from nocturnal symptoms, the physical drain of chronic gut discomfort, and the shared neurological pathways with fibromyalgia.
What's Not IBS — When to Be Concerned
IBS is diagnosed after ruling out structural disease. The following features should prompt investigation for other conditions:
Blood in stool — NOT a feature of IBS; warrants colonoscopy
Weight loss — NOT a feature; warrants investigation
Symptoms beginning after age 50 — needs investigation to exclude colorectal cancer
Family history of colorectal cancer or IBD — lower threshold for investigation
Fever — not IBS
Nocturnal symptoms waking from sleep — not typical of IBS; functional gut disorders generally spare sleep
Severe and progressive symptoms — IBS fluctuates; steadily worsening symptoms suggest organic disease
What Triggers IBS
Specific foods: the most individually variable factor. Common triggers include:
FODMAPs (Fermentable Oligosaccharides, Disaccharides, Monosaccharides and Polyols): a group of short-chain fermentable carbohydrates that poorly absorbed in some people produce gas and osmotic effects in the large intestine. High-FODMAP foods include onion, garlic (very high FODMAP — a significant issue for Indian cooking), wheat, dal and legumes in large quantities, certain fruits (mango, watermelon, peach, apple).
Fatty and fried foods: delay gastric emptying and increase gut motility irregularly
Spicy food: capsaicin can irritate gut lining in sensitive individuals
Caffeine: stimulates colonic motility — can trigger urgency
Alcohol: disrupts gut motility and microbiome
Dairy (lactose): lactose intolerance can mimic or worsen IBS
Stress and anxiety: the gut-brain axis in IBS is dramatically sensitive to psychological stress. Examinations, relationship conflict, work pressure, financial anxiety — all trigger or worsen IBS symptoms. This is not the person being "weak" or "imagining" symptoms — it's a direct neurobiological link through the enteric nervous system.
Gut infections: a significant proportion of IBS cases (post-infectious IBS) begin after an acute gastroenteritis episode — the infection triggers lasting changes in gut motility and sensitivity. Food poisoning, typhoid recovery, and viral gastroenteritis can all precede IBS onset.
Antibiotics: disrupt the gut microbiome and can trigger or worsen IBS.
Hormonal changes: women with IBS often notice symptoms are worse premenstrually — the gut has estrogen and progesterone receptors that affect motility.
Management
IBS is managed rather than cured. The goal is reducing symptom frequency and severity to a level that allows normal function.
Dietary modifications
Low-FODMAP diet: the most evidence-based dietary intervention for IBS. Involves temporarily eliminating high-FODMAP foods for 4–6 weeks, then systematically reintroducing them to identify individual triggers. The challenge in an Indian context: onion and garlic — foundational to Indian cooking — are very high-FODMAP. Alternatives: asafoetida (hing) in oil for the flavour base; the green parts of spring onions (low-FODMAP); garlic-infused oil (the FODMAP compounds don't pass into oil).
A formal low-FODMAP trial is best guided by a dietitian — it's complex and the reintroduction phase is where the individual learning happens.
Regular meal timing: eating at consistent times and not skipping meals reduces gut motility irregularities.
Adequate fibre: for IBS-C. Soluble fibre (isabgol, oats, dal) is better tolerated than insoluble fibre (bran) which can worsen bloating in IBS. Increase slowly.
Adequate hydration: particularly for IBS-C.
Stress management
Given the gut-brain axis dysregulation at the heart of IBS, stress management is a medical intervention:
Cognitive behavioural therapy (CBT): the most evidence-based psychological intervention for IBS — reduces symptom severity and anxiety about symptoms
Yoga and pranayama: accessible in India; reduces both stress and directly modulates the autonomic nervous system's gut effects
Regular exercise: improves gut motility, reduces stress, improves sleep
Probiotics
Specific probiotic strains — Lactobacillus rhamnosus, Bifidobacterium infantis, and multi-strain preparations — have evidence for reducing IBS symptoms, particularly bloating and pain. Regular plain curd provides some benefit; targeted probiotic supplements are more reliable for specific strain delivery. A 4–8 week trial of a quality probiotic is worthwhile.
Medications by subtype
For IBS-C:
Fibre supplements (isabgol)
Osmotic laxatives (polyethylene glycol, lactulose) — gentler than stimulant laxatives
Antispasmodics (mebeverine, hyoscine) for cramping alongside constipation
For IBS-D:
Loperamide (Imodium) for acute diarrhoea and before events where urgency would be problematic — not for regular use
Antispasmodics for cramping (mebeverine, hyoscine, dicyclomine)
Rifaximin (prescription) — non-absorbed antibiotic for IBS-D with evidence for improvement
For pain:
Low-dose tricyclic antidepressants (amitriptyline 10–25 mg at night): reduce gut sensitivity and improve sleep without being antidepressant doses
Low-dose SSRIs: sometimes used for IBS-D patients
Care at Prakash Hospital Noida
At Prakash Hospital Noida, our physicians and gastroenterologists evaluate IBS — including investigation to rule out structural disease (blood tests, stool tests, and colonoscopy where indicated), dietary counselling, and appropriate treatment. Mental health support coordination for the stress component of IBS management is available.
Whether you live in Sector 18, Sector 62, Greater Noida West, or anywhere in the NCR, Prakash Hospital Noida is a trusted name for IBS, gastroenterology, and digestive health in Noida.
We offer expert care across key specialties, including Medicine, Cardiology, Orthopaedics, ENT, Gynaecology, and more—delivering trusted treatment under one roof.
Read your lipid profile line by line: total cholesterol, LDL, HDL, triglycerides, non-HDL and VLDL. Learn the LDL formula, targets by risk and when to retest.
लिवर सिरोसिस के लक्षण, कारण, स्टेज और इलाज जानें। पीलिया, पेट में सूजन और थकान को नजरअंदाज न करें। Prakash Hospital में पाएं एडवांस लिवर केयर और गैस्ट्रोएंटरोलॉजी उपचार।